
Treating Dark Spots and Sun Damage
Here's the thing that doesn't fit on a brochure. Most treatments for a dark spot work by injuring your skin on purpose. And injury is one of the main reasons skin makes pigment in the first place.
That's not a reason to avoid treatment. It is the reason that pigment work rewards a cautious provider and punishes an eager one, and it's why the same treatment that clears a mark on one patient leaves a bigger one on somebody else.
If your skin tans easily rather than burning, this page is the one I'd want you to read twice.
Why your skin makes the mark
Pigment cells sit in the lower part of your epidermis and respond to signals. Ultraviolet light is one signal. Inflammation is another, and they use the same machinery.
That second one has a name: post-inflammatory hyperpigmentation. A spot, a scratch, a burn, an aggressive treatment, anything that provokes an inflammatory response can leave a flat brown patch behind once the original thing has healed. It isn't a scar. It's a stain, and stains fade, slowly, on their own timeline.
People with more melanin to work with have more pigment response available, so the mark tends to be darker and stays longer. The Fitzpatrick scale is the rough shorthand providers use for this, and a provider who asks about how your skin responds to sun and to past injuries is doing exactly the right thing.
Sun damage and melasma are not the same problem
Two things get filed under "dark spots" and they behave differently.
Sun-driven spots, the flat brown patches on the face and the backs of hands, are accumulated damage. They're generally localized, stable, and reasonably cooperative with treatment.
Melasma is a different animal. It comes in larger symmetrical patches, it's strongly influenced by hormones as well as light, and it has a habit of coming back and of flaring in response to heat and to treatment. Melasma is where a heavy-handed approach does the most damage, and it's the diagnosis most often missed by someone who glanced at your face for thirty seconds.
If nobody has told you which one you have, that's the first appointment, not a detail to sort out later.
The treatments, and the order of caution
Sunscreen, daily, is not the boring preamble. It's the treatment. Everything else on this list fails without it, because pigment cells that keep getting the light signal keep making pigment, and you'll be repaving a road that's still under traffic.
Topicals come next in most sensible plans. Prescription-strength options work on the pigment pathway directly, over months, with the lowest risk of provoking the thing you're trying to fix. Slow is a feature here.
Chemical peels can work well, and depth is everything. A light peel does less and risks less. A deeper peel does more and, on pigment-prone skin, can trigger a rebound that lasts longer than the original spot. A provider who suggests starting light and reassessing is not being timid.
Microneedling has a role, mostly for texture alongside pigment, and carries the same inflammation caution.
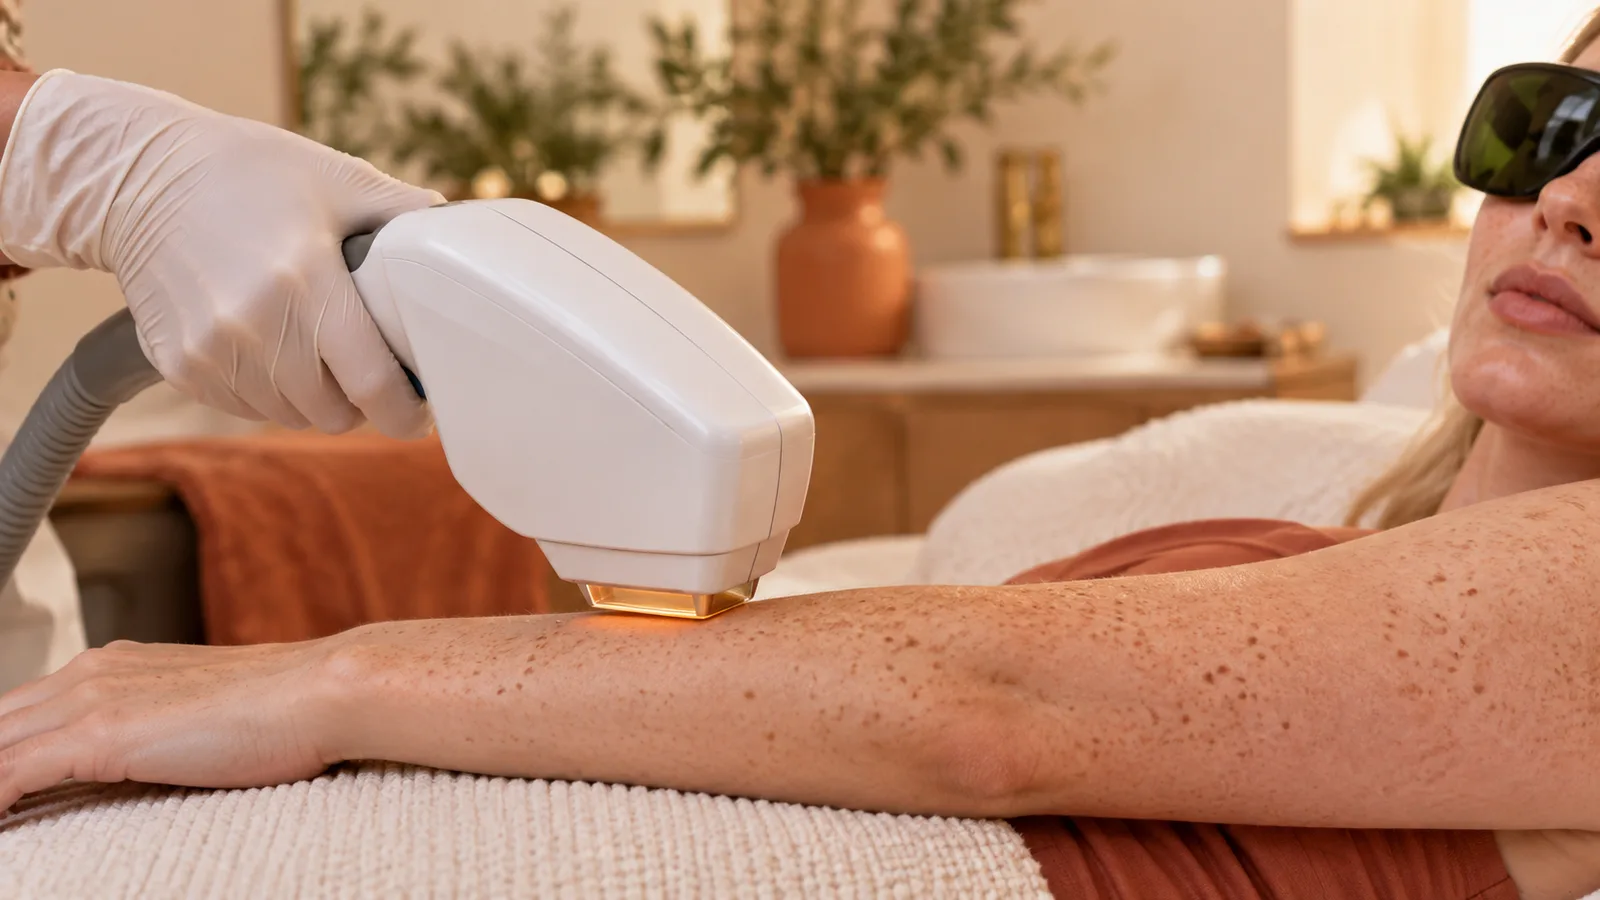
Lasers and light devices are the highest-leverage and the highest-risk category. Some wavelengths and settings are appropriate for deeper skin tones and plenty are not. Being treated with the wrong device here is one of the few ways to make a pigment problem meaningfully worse in a single afternoon.
What a cautious provider sounds like
They ask what your skin did the last time it was injured. They ask about pregnancy, hormonal contraception, and any medication that affects light sensitivity. They talk about a test patch. They quote you a series and a timeline in months. They tell you melasma is managed rather than resolved, if that's what you have.
What an overconfident provider sounds like: one session, a single device for every complexion, no test patch, and a before-and-after folder instead of a plan.
You're allowed to ask directly whether they treat your skin tone often. It's a fair question, it's easy to answer, and the reaction to being asked is informative on its own.
The timeline nobody likes
Topical pigment work is measured in months, not weeks. Peels and needling work in series with weeks between them. Post-inflammatory marks from an old spot can take many months to fade with no treatment at all, which means some of what you'd credit to a treatment was going to happen anyway.
The practical consequence is that you should judge a plan at three months, not at three weeks, and you should be suspicious of any plan that asks you to decide faster than that.
Getting it looked at
A pigment problem deserves an in-person assessment before anything is booked, partly for the diagnosis and partly because the right treatment depends on how your skin behaves rather than how the patch looks in a photo.
A lot of people cast the net past North Hudson for that assessment, and the ride over to Hoboken is not much of an obstacle. Whether you ask somewhere on Bergenline or look up chemical peels hoboken and take the ride, what matters is that somebody qualified looks at your skin in daylight, names what you have, and starts with the lightest peel that could do the job. Membership listings like Home - Hudson County Chamber of Commerce will confirm a place exists and answers its phone before you spend an afternoon on it. That's the whole of what they're good for.
One last practical note, because it comes up constantly: if you're outdoors for work or classes most of the day, say so before a plan is built. A schedule spent walking between buildings at a campus like Hudson County Community College is a different sun exposure than an office, and it should change what gets recommended and when.
Start with the diagnosis, start light, and give it three months before you judge it.